

Short answer
Switch from Excel to clinic software once any of four things is true: more than one person edits the same file, you pay DF to employed doctors, you open a second branch, or a patient exercises a PDPA right. Before that, Excel works for one doctor. Its weakness: it can't prove who opened which patient record.
Key points
- Excel is fine for one doctor, one branch and one person editing the file.
- PDPA doesn't ban spreadsheets, but the clinic must be able to show who accessed patient data.
- Google Sheets fixes concurrent editing and lost files, not per-person access or silent formula errors.
- Price Excel by the hours spent on repeated monthly work, not at zero baht.
- Move patient records and appointments first, and keep the old files read-only for about three months.
Can a Clinic Still Run on Excel?
Yes, if the clinic has one doctor, modest patient volume and nobody else editing the file. The moment to switch arrives before Excel breaks: when more than one person edits the same file, you start paying DF to employed doctors, you open a second branch, or a patient exercises a PDPA right.
The reason to move has little to do with what Excel can calculate. Patient records are sensitive data under the law, and a spreadsheet makes it very hard to prove who opened what. That responsibility sits with the clinic, not with whoever built the file.
What Does Excel Genuinely Do Well?
Starting in Excel is a sensible decision. It costs nothing extra, everyone already knows it, you can restructure it the moment you want to, and nobody has to install anything for you.
A new clinic that doesn't yet know its real workflow usually spends less by starting in a spreadsheet and migrating later than by buying a large system on day one and discovering it doesn't match how the clinic works. So this guide doesn't argue Excel is bad. It shows where the line sits.
What Are the Signs a Clinic Has Outgrown Excel?
One: more than one person edits the same file. The symptom is filenames ending in final, final-real, use-this-one, and nobody can say for certain which file holds the truth.
Two: you pay DF to employed doctors. That means pulling what each patient actually paid, splitting by procedure, applying each doctor's agreed percentage and handling withholding tax. A spreadsheet can do it, but it must be redone every month, and a mistake is a mistake about money owed to a doctor.
Three: you open a second branch. Two spreadsheets are two sets of data to merge by hand whenever you want the full picture, and patient numbers usually start colliding in the first month.
Four: patients ask for their history. When someone returns after two years, searching files split by year or month takes longer than a patient will wait at the counter.
Five: someone exercises a PDPA right, asking to see, correct or delete their data. You must answer within the timeframe the law sets, which means knowing everywhere that data lives. That is hard when files have been forwarded through chat.
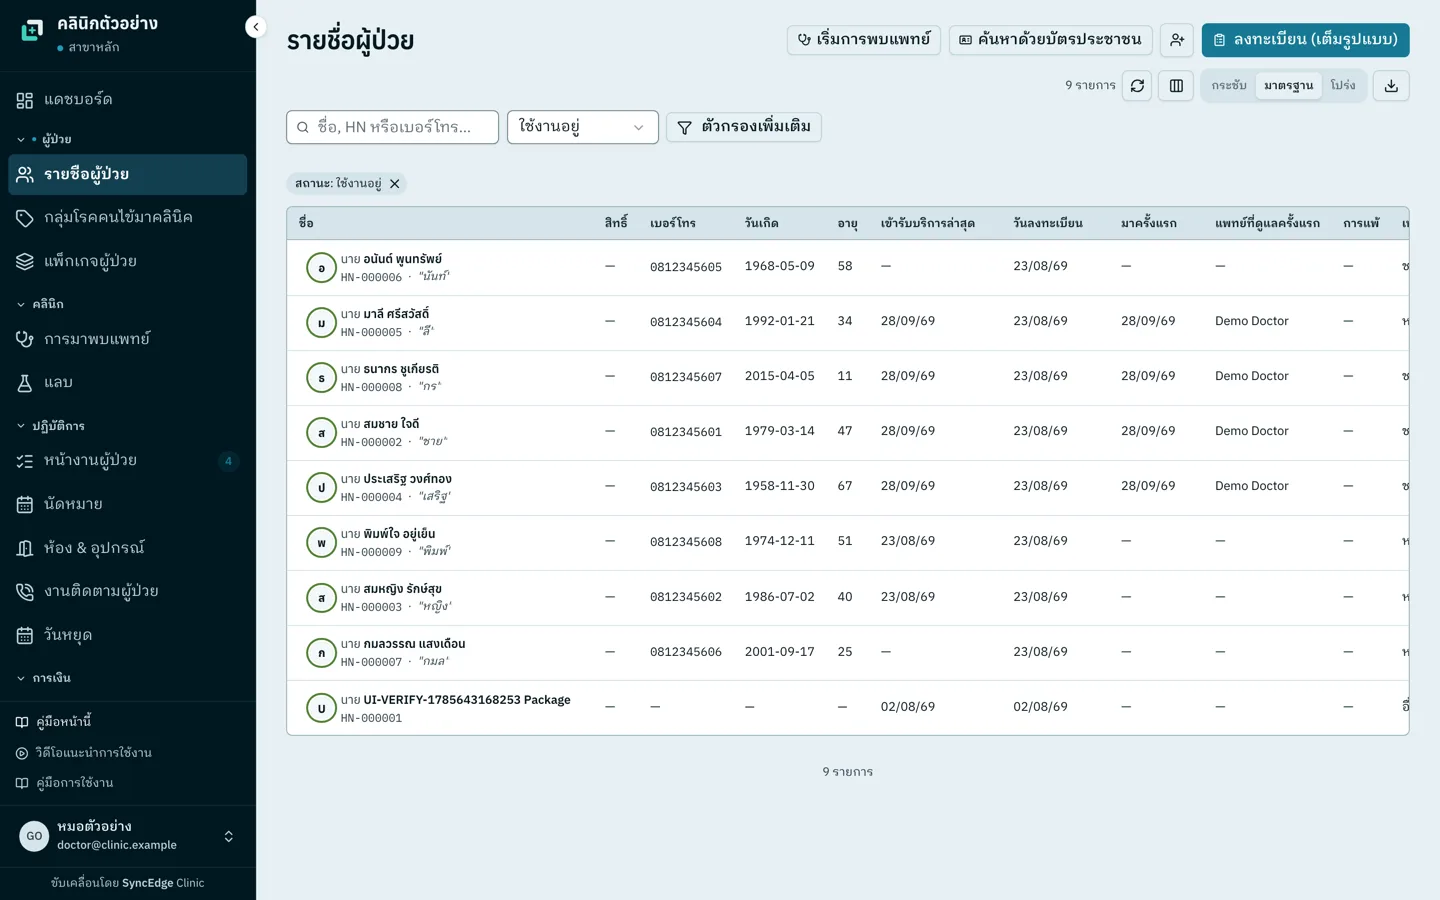
Does Keeping Patient Data in Excel Break PDPA?
No, PDPA does not prohibit Excel. It requires the data controller to have appropriate security measures and to be able to demonstrate them, and demonstrating is where spreadsheets struggle.
Try answering these about the file you use today: who opened it in the past month; who changed this number, and when; which other machines hold a copy; whether a staff member who left today could still open the copy sent in chat; and, if a patient asked for deletion, how you would know every copy was gone.
These are hard to answer with a spreadsheet, however careful the staff are, because the file was never built to record what was done to it. Software designed for patient records logs every access and change itself, sets permissions per person, and revokes access for real when you revoke it.
Excel and Clinic Software, Side by Side
Excel still wins on flexibility and cost. Clinic software wins where several people need the same data, where you must be able to look back and verify, and where a task repeats every month and has to be right.
Read the table for the rows that describe a problem you have right now. If none do, it isn't time yet.
| Excel / spreadsheet | Clinic software | |
|---|---|---|
| Monthly cost | Effectively none | A subscription fee |
| Several people at once | Conflicts, merged by hand | Works concurrently |
| Knowing who changed what | No record | Logged every time |
| Per-person permissions | Limited | Set by role |
| Finding old patient history | File by file | Found immediately |
| DF and withholding tax | By hand, every month | Calculated automatically |
| Combining branches | Merged manually | Consolidated view |
| Answering PDPA requests | Chase every copy | An auditable record exists |
When Does a Google Sheets Setup Stop Being Enough?
Google Sheets stops being enough once more people have access, once you need to show under PDPA who looked at which patient, and once the formulas behind DF and stock start drifting unnoticed. It does fix two of Excel's problems: several people can edit at once, and the file doesn't die with one computer.
First, sharing. Clinics usually share one sheet with everyone, from doctors to part-time staff, and everyone sees the whole file. Shared as anyone-with-the-link, the day that link is forwarded in a chat, every patient record goes with it, and staff who have left may still hold downloaded copies.
Second, the access record. Version history shows who changed which cell and when, but not who looked at which patient, and one sheet can't show different people different patients. Section 37(1) of the PDPA still requires the clinic to have measures against unauthorised access.
Third, formulas. DF in a sheet depends on formulas pointing at the right ranges. Someone inserts a row, drags a formula short or types over a formula cell, and the totals go wrong silently. Stock is the same: the calculated balance parts company with the shelf the first time someone forgets to record a dispense, and nobody finds out until the month-end count.
If only one or two people edit the sheet, no employed doctors need DF, and the sheet is shared with named accounts rather than by link, Google Sheets can still carry a small clinic. Past that, clinic software that sets access per person and calculates DF and stock costs less than the hours spent hunting broken formulas.
Shared Google Sheet
- Everyone with access sees the whole file
- A forwarded link exposes every record
- History shows edits, not who viewed a patient
- DF and stock formulas break silently
Clinic software
- Access set per person and role
- Revoked access stops working at once
- Every access and change is logged
- DF and stock calculated by the system
Sources
What Does Excel Really Cost a Clinic?
Excel's visible cost is zero. Its real cost is the time spent on work that repeats every month, plus a risk that is hard to price until the day it happens.
Time it honestly for one month: closing daily totals, calculating DF for each doctor, digging out old patient histories, merging files from different machines, and redoing work when a file is corrupted or overwritten.
Multiply those hours by the hourly cost of whoever does the work, then compare it with a monthly subscription. Many clinics find the two figures closer than expected, and that still leaves the risk to patient data unpriced.
How Should You Start Moving Off Excel?
Start with patient records and appointments, not everything at once: they are used daily and show results fastest. Historical reporting can follow later.
Keep the old spreadsheets read-only for about three months rather than deleting them, and put all new work into the new system only. If people keep editing the old files too, you are back to two versions of the truth.
Put one person in charge of the move and start in a quieter week. SyncEdge Clinic has no setup fee on any tier, and the 2-month trial needs no credit card, which is enough to import a hundred real records and test the workflow before committing.
- Name an ownerOne person runs the move; start in a quieter week.
- Patients and appointments firstImport the records used every day; reports can wait.
- Test with real recordsImport about a hundred real patients during the trial.
- New work in one placeFrom day one, all new entries go into the new system only.
- Old files read-onlyKeep the spreadsheets for about three months, then retire them.
Has Your Clinic Reached the Switching Point?
- More than one person edits the same file each day
- More than one file has "final" in its name
- You pay DF to employed doctors
- You have a second branch, or will open one this year
- Finding an old patient's history takes longer than they'll wait
- Patient files have been sent by chat or copied to a USB drive
- You can't say who viewed patient data last month
- A patient has asked to see, correct or delete their data
Frequently asked questions
Is keeping patient data in Excel against PDPA?
Not in itself. PDPA doesn't specify which software to use; it requires appropriate security measures that the clinic can demonstrate. The difficulty with spreadsheets is proving who accessed the data and controlling copies once they have spread through chat or USB drives. That responsibility sits with the clinic as data controller, not with the person who built the file.
How small does a clinic have to be to stay on Excel?
One doctor, no employed doctors needing DF, one person editing, one branch, and the file on a password-protected machine that is backed up regularly. Within those limits Excel still works. The tipping point usually comes from how many people need the same data, well before patient numbers become the issue.
Can I bring old Excel data into clinic software?
Yes, if the file has reasonable structure. Line up the columns first (name, surname, phone, date of birth, patient number), clean duplicates, then import. With SyncEdge Clinic, every tier imports from Excel/CSV through the Migration Center using Thai templates, at no charge, so you can test a hundred real records during the trial.
Is clinic software much more expensive than Excel?
Subscriptions start in the hundreds to low thousands of baht a month for a small clinic; SyncEdge Clinic starts at ฿990 a month for Solo, 7% VAT included. The fair comparison isn't Excel's zero. It is the hours spent on repeated work each month, such as daily totals and DF, multiplied by the cost of the person doing it.
Would Google Sheets solve this instead of Excel?
Partly. It genuinely helps with concurrent editing and backups, and it beats files forwarded through chat. But it still doesn't give per-patient access control, a record of who viewed which patient, or clinic work like DF calculation and medical certificates, and its formulas can still break without warning.
Is there a free clinic template for Excel, and how far does it go?
Free Excel and Google Sheets clinic templates are easy to find, and they genuinely work as a patient register, appointment book or income log for a one-doctor clinic. Their limits: no per-person access, no record of who viewed which patient, and DF or stock formulas that can break silently. If medical records live in the file, a 2015 Thai Ministerial Regulation also requires a backup system.